
- The focused questions:
- Is Right Ventricular Dilation Suggestive of Pulmonary Embolism ?
- Tips
- Dilated right ventricle is best seen in PSAX and A4CH
In the context of suspected pulmonary embolism, ultrasound can provide crucial diagnostic information by assessing right ventricular (RV) dilation. A dilated RV suggests increased pressure in the pulmonary arteries, often caused by a pulmonary embolism obstructing blood flow to the lungs. Key ultrasound findings include an enlarged RV compared to the left ventricle (LV), abnormal septal motion, and in some cases, visible clot or poor RV function.
Confirming Pulmonary Embolism Suspicion:
- Right Ventricular Dilation: The RV appears larger than the LV, indicating pressure overload.
- Septal Flattening or Paradoxical Motion: The interventricular septum may bow towards the LV due to increased RV pressure.
- McConnell’s Sign: A specific pattern of RV dysfunction where the apex contracts normally while the free wall is hypokinetic, seen in some cases of pulmonary embolism.
Ruling Out Significant RV Dysfunction:
- Normal RV Size and Function: The RV should not appear larger than the LV, and the septum should remain in a normal position.
The clips below demonstrate different cases of RV dilation, helping you to recognize these key signs in patients suspected of having pulmonary embolism.
SC – A4CH – PLAX – PSAX
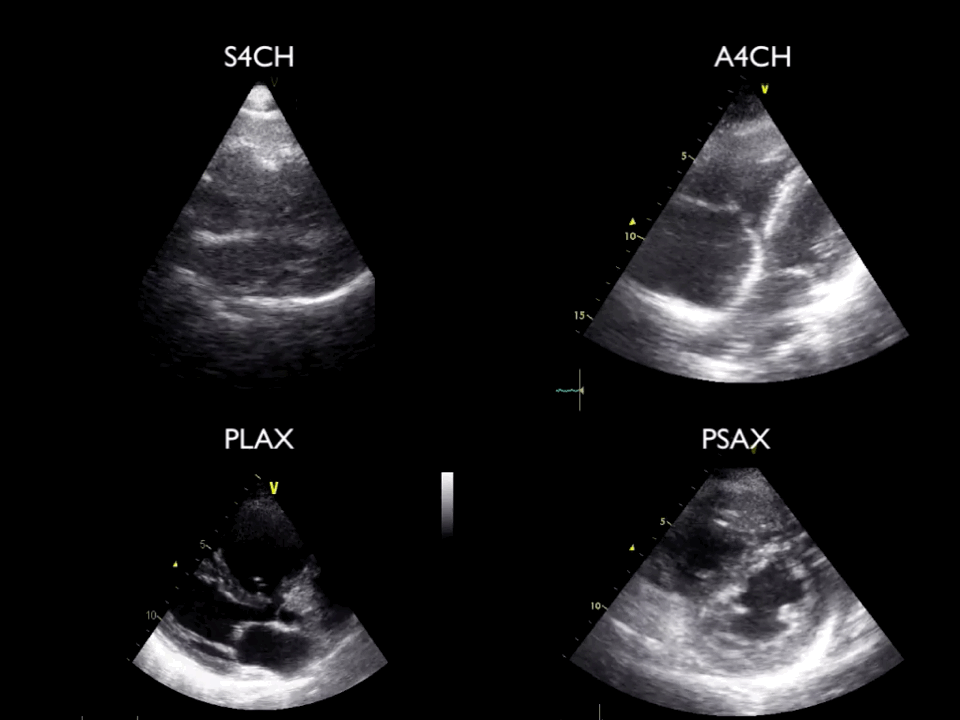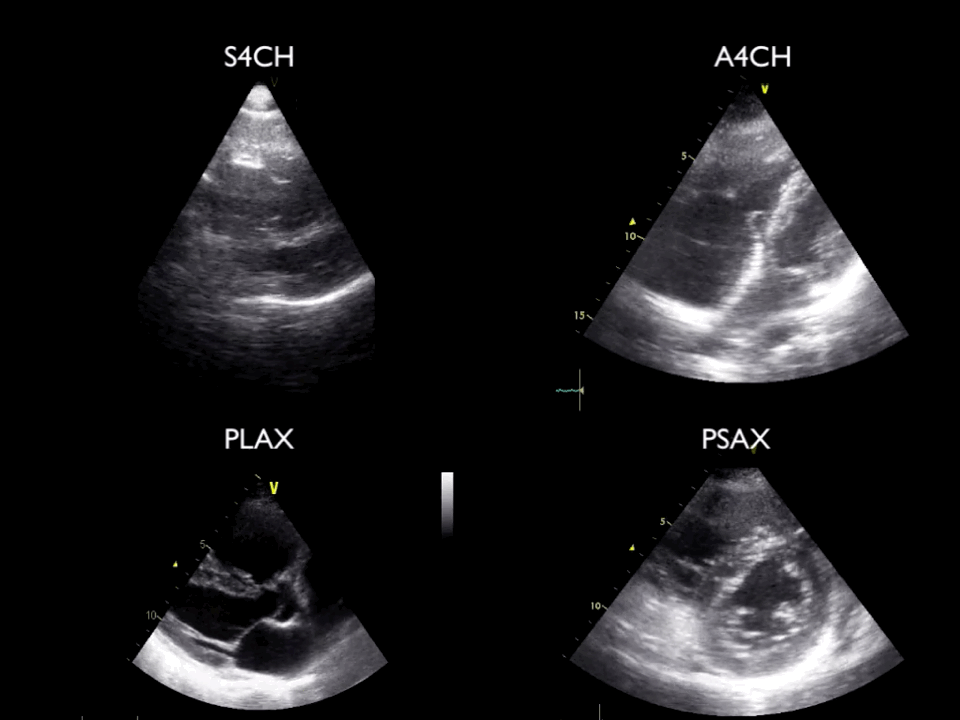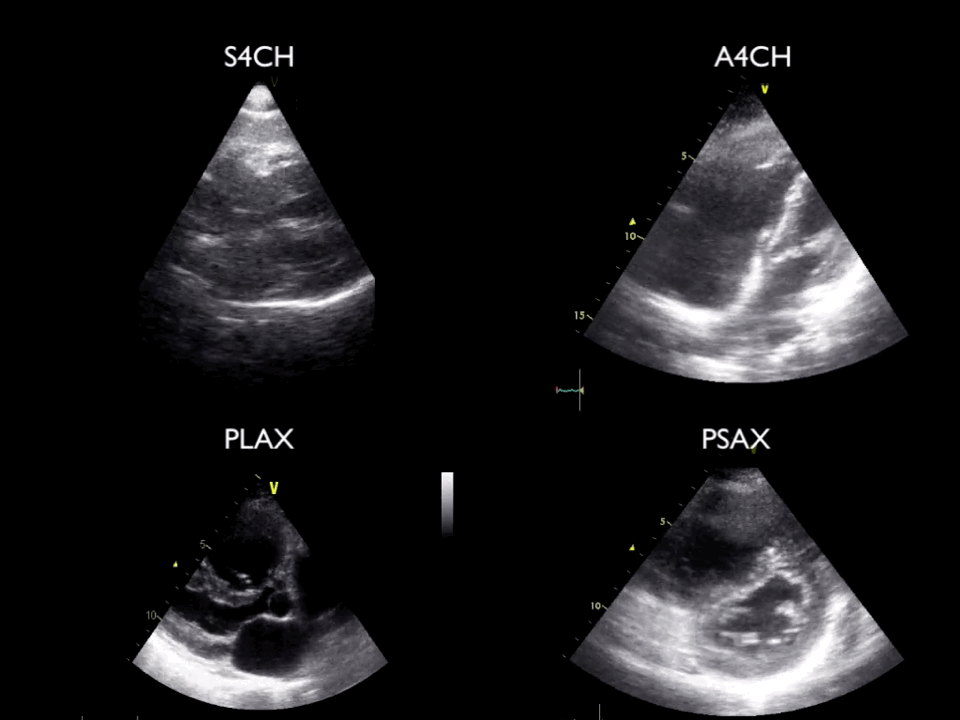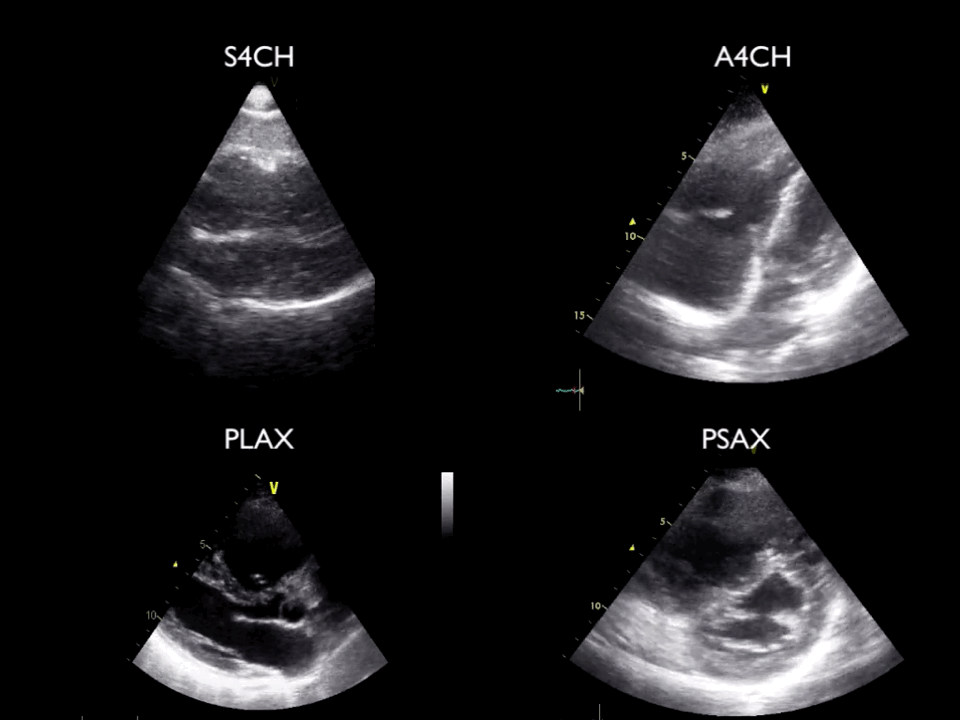
Dilated Right Ventricle in All 4 Cardiac Views: Ultrasound clip showing a dilated right ventricle in four cardiac views upper left subcostal view upper right apical 4-chamber view lower left parasternal long-axis view lower right parasternal short-axis view the pathologic dilation is most clearly seen in the apical 4-chamber and parasternal short-axis views where the right ventricle appears significantly enlarged suggesting pulmonary embolism
A4CH
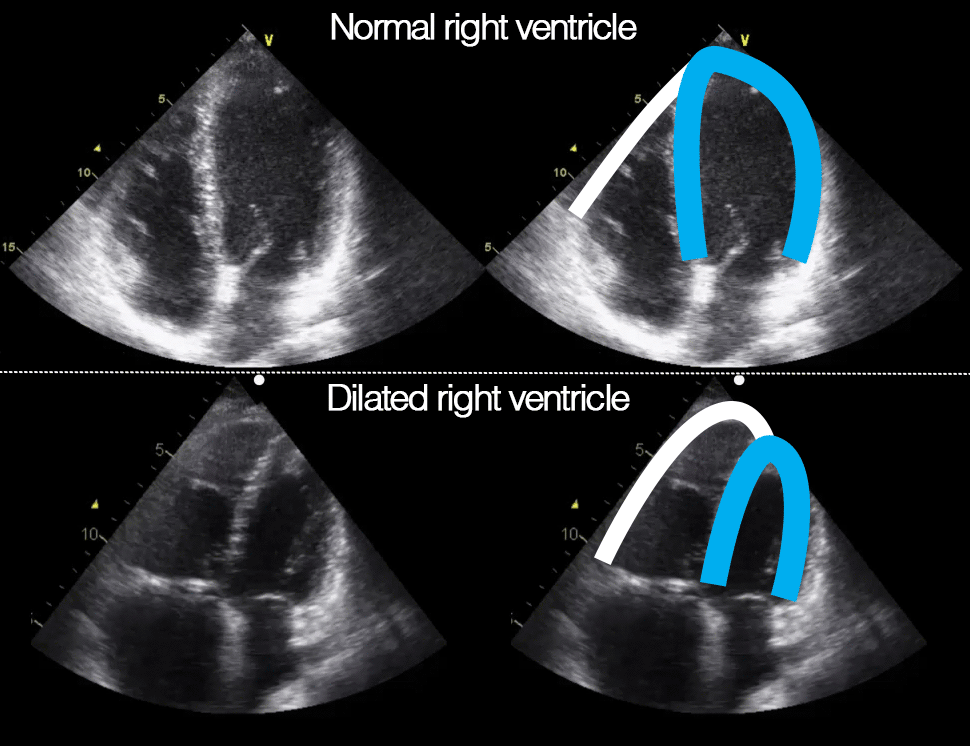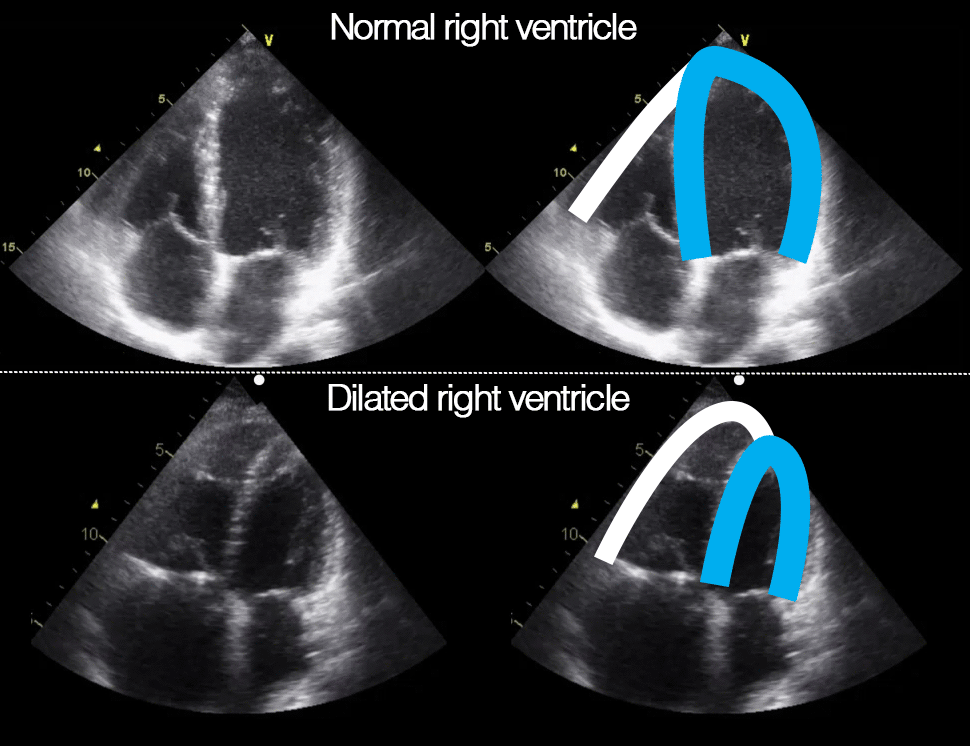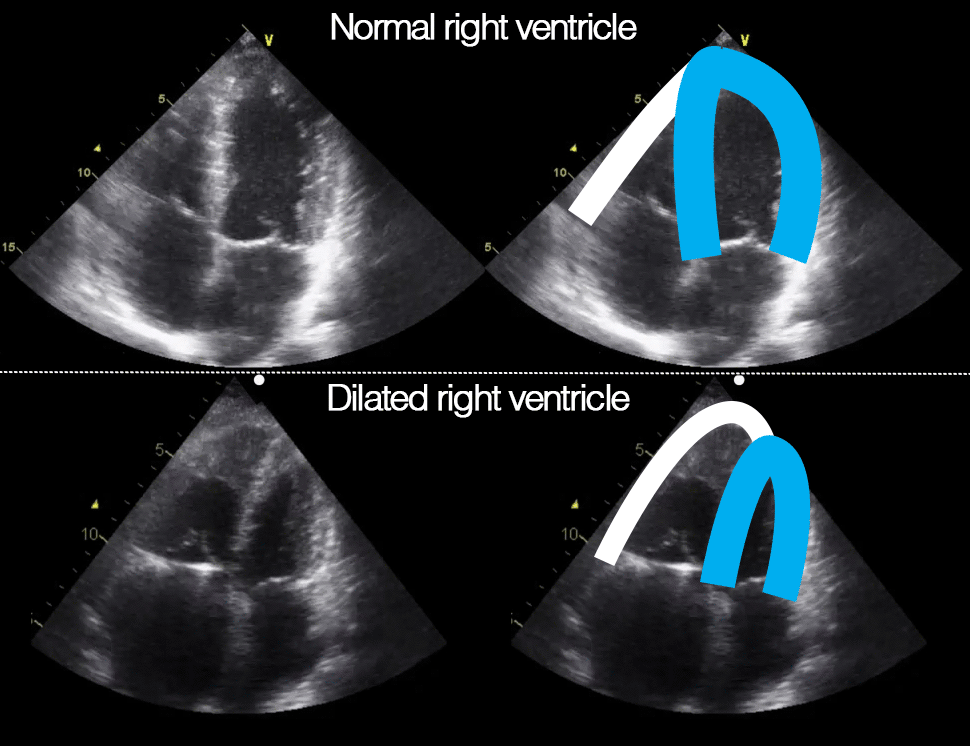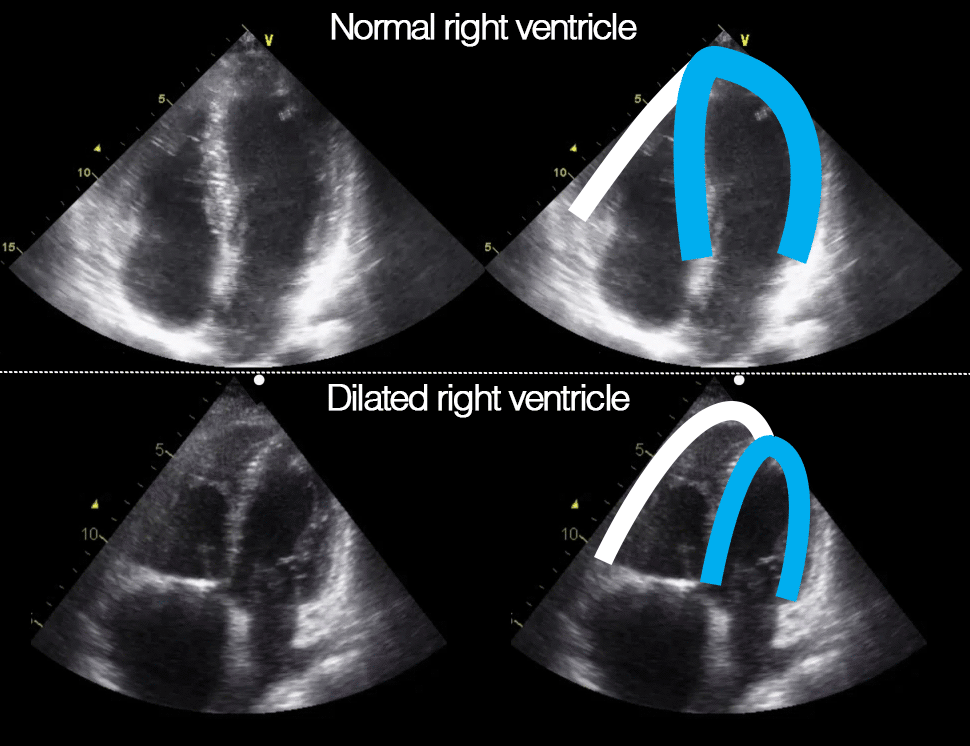
Comparison of Normal and Dilated Right Ventricle in A4CH View: Ultrasound clip showing a comparison of normal and dilated right ventricles in the apical 4-chamber (A4CH) view. Upper row demonstrates normal findings, and lower row shows findings in a dilated right ventricle. In the upper normal clips, left is the raw clip and right shows an overlay with a blue line over the left ventricle illustrating thickening during systole and a white line showing the small straight free wall of the right ventricle. Lower row demonstrates a dilated right ventricle. Left is the raw clip and right shows the overlay with the blue line demonstrating a smaller left ventricle and the white line bulging out, showing the dilated right ventricle.
SC
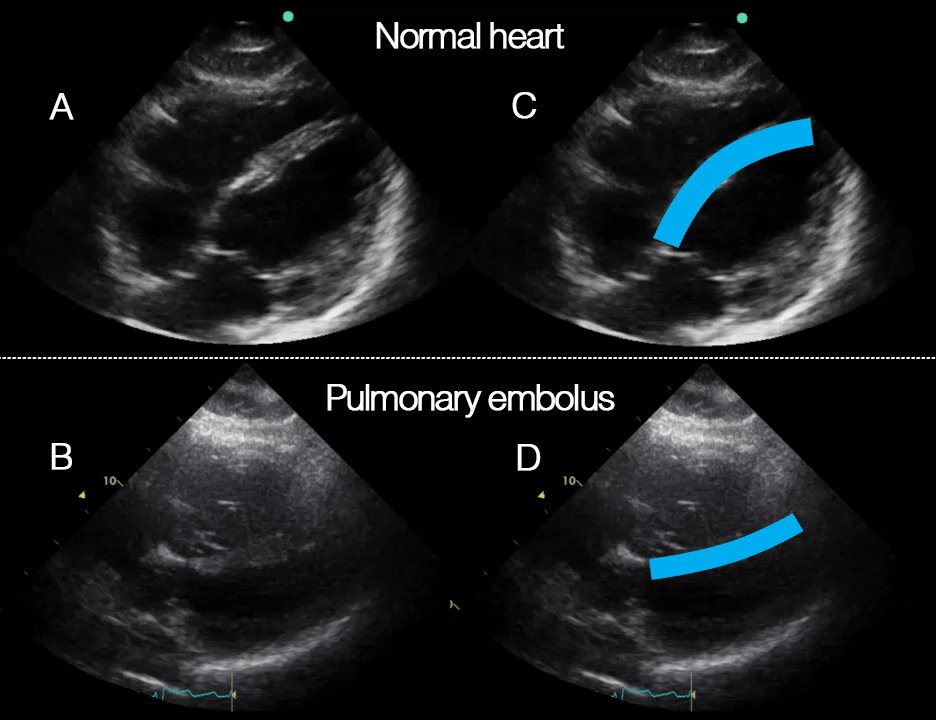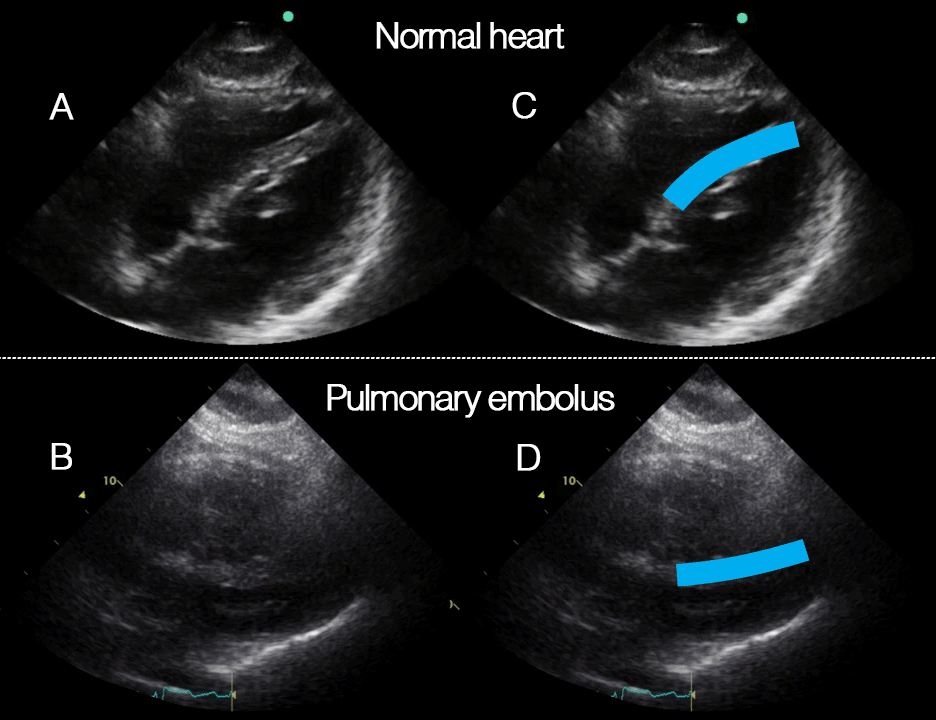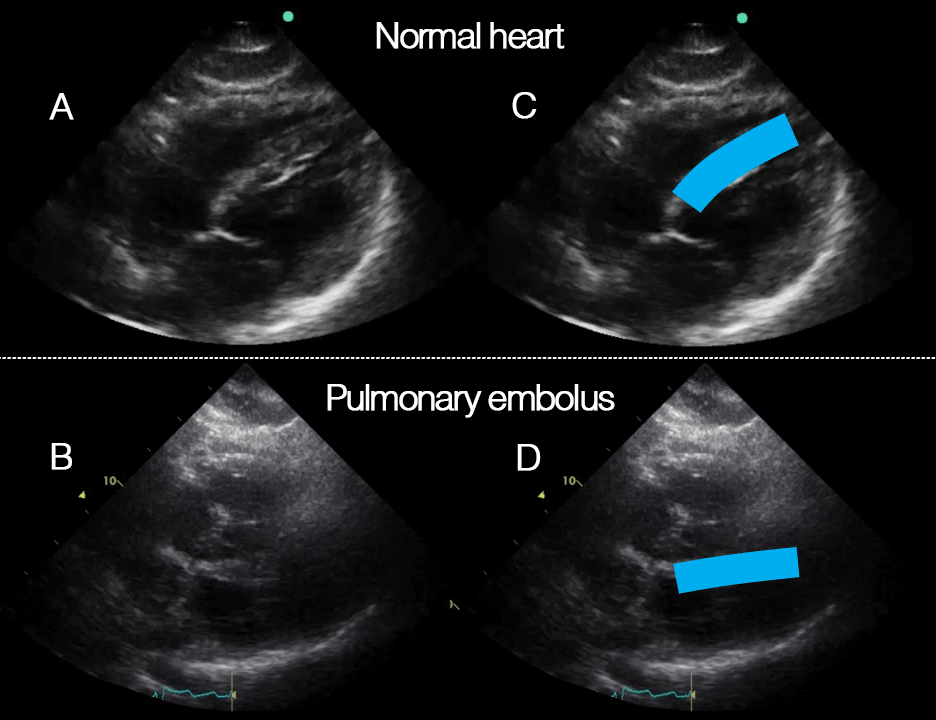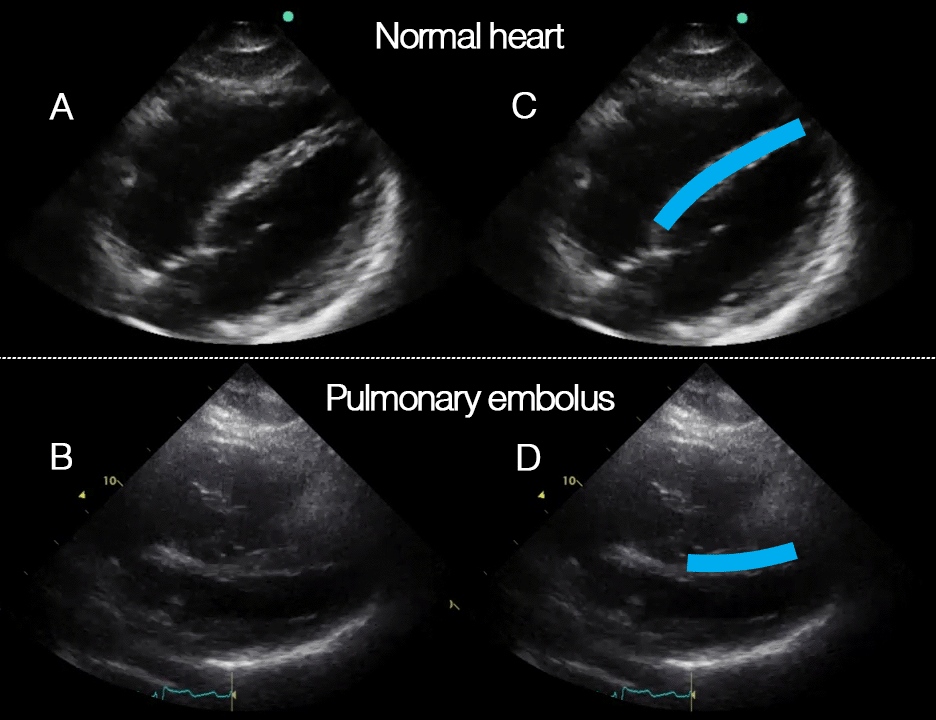
Septal Flattening or Paradoxical Motion in A4CH View: Ultrasound clip showing a comparison of normal and abnormal septal motion in the apical 4-chamber (A4CH) view. Upper row demonstrates normal findings, and lower row shows abnormal septal flattening due to increased right ventricular pressure. In the upper normal clips, left is the raw clip and right shows an overlay with a blue line illustrating normal septal motion. In the lower row, left is the raw clip and right shows the overlay with the blue line bowing towards the left ventricle during systole, demonstrating septal flattening or paradoxical motion.
A4CH

A4CH View with Enlarged Right Ventricle and Septal Flattening: Apical 4-chamber (A4CH) view showing an enlarged right ventricle on the left side of the image. The interventricular septum is flattened throughout the cardiac cycle, indicating increased right ventricular pressure.
PSAX
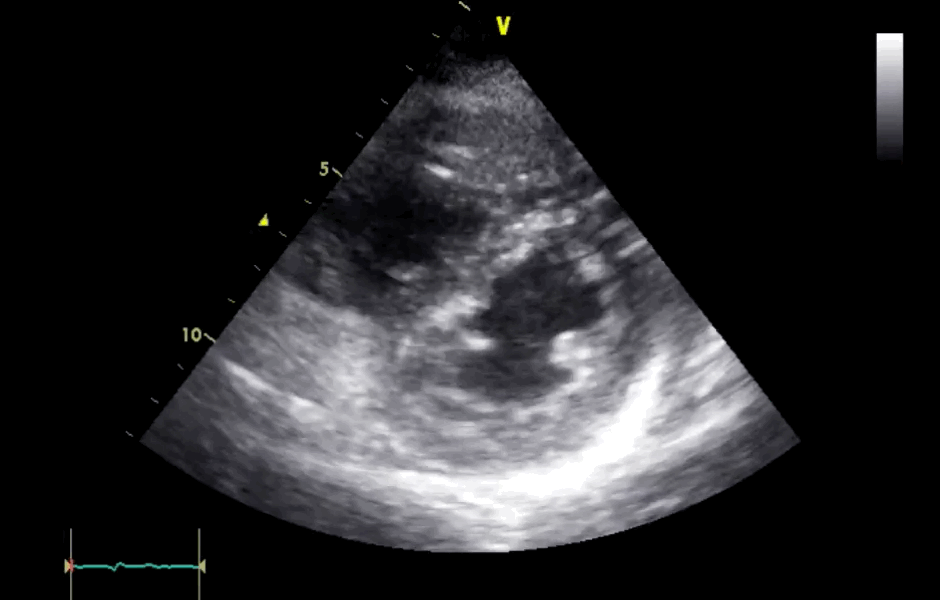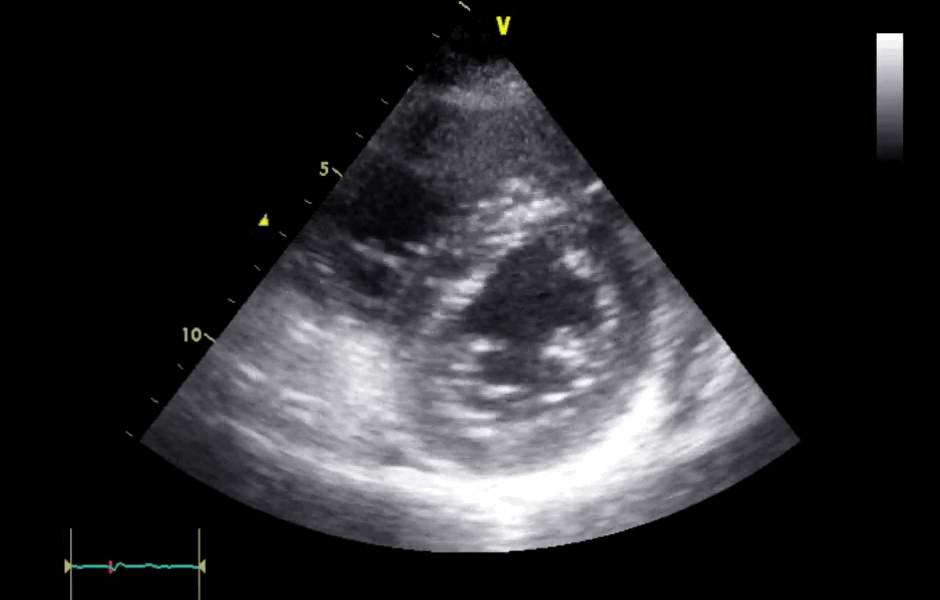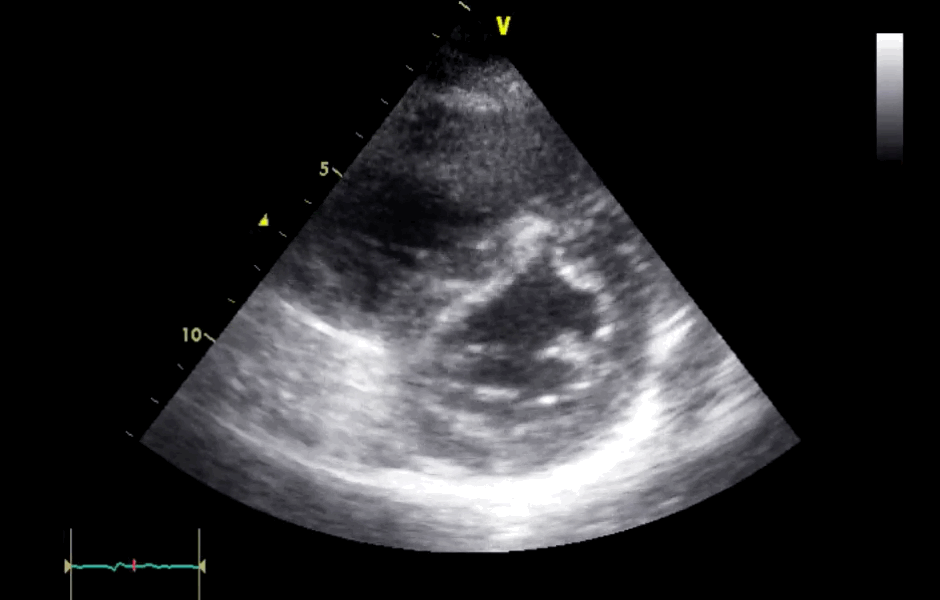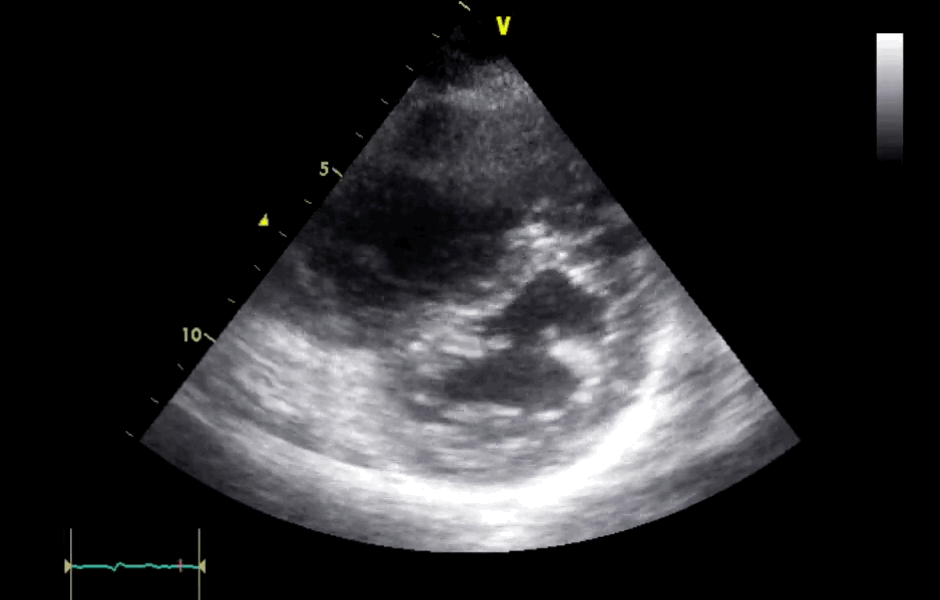
PSAX View with Enlarged Right Ventricle and D-shaped Left Ventricle: PSAX view showing an enlarged and dilated right ventricle. The left ventricle appears D-shaped due to the pressure from the dilated right ventricle, a classic sign of right ventricular pressure overload.
PSAX

PSAX View with Enlarged Right Ventricle and More Compressed D-shaped Left Ventricle: PSAX view showing an enlarged and dilated right ventricle. The left ventricle appears even more compressed and D-shaped, indicating significant right ventricular pressure overload.
PLAX
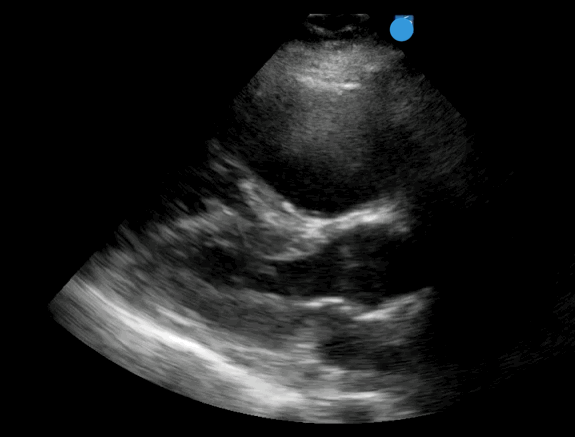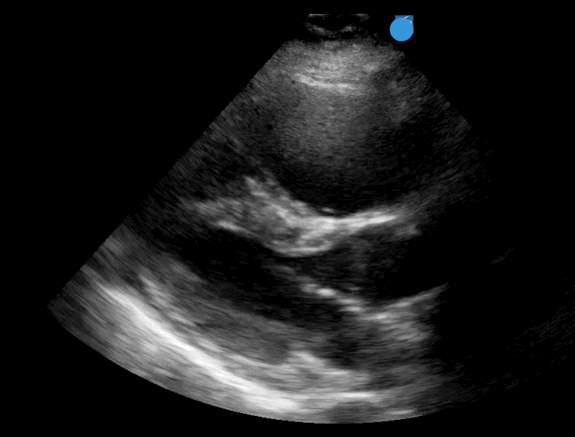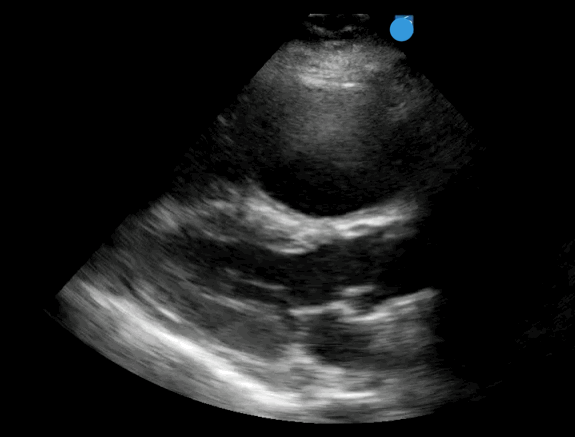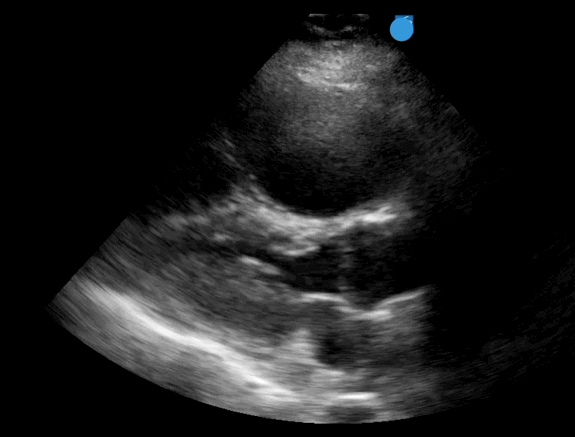
PLAX View with Dilated Right Ventricle: PLAX view showing a dilated right ventricle, visible at the top of the image. This finding suggests right ventricular pressure overload and raises suspicion for pulmonary embolism.
PSAX
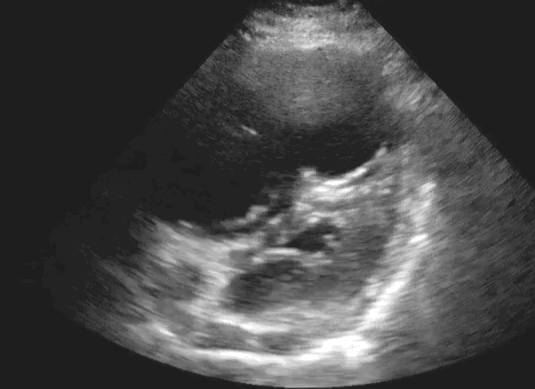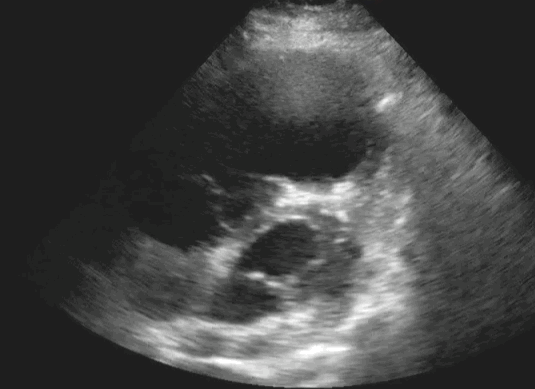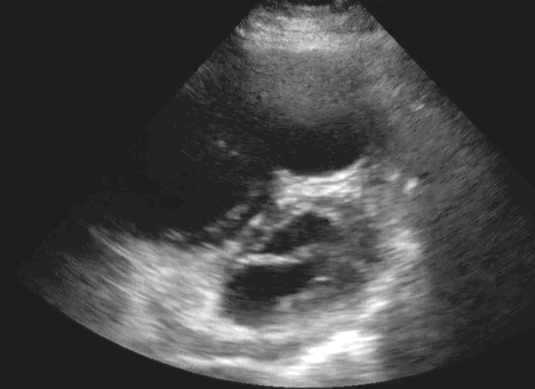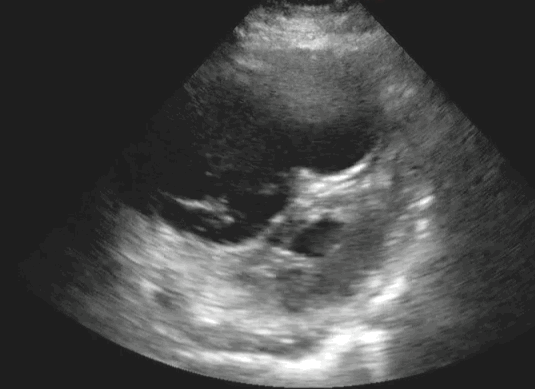
PSAX View with Huge Right Ventricular Dilation and D-shaped Left Ventricle: PSAX view showing a massively dilated right ventricle. The left ventricle is D-shaped and shows a significantly reduced volume, indicating severe right ventricular pressure overload.
A4CH

A4CH View with Severely Dilated Right Ventricle, Flattened Septum, and McConnell’s Sign. Apical 4-chamber (A4CH) view showing a severely dilated right ventricle and reduced left ventricle. The interventricular septum is flattened throughout the cardiac cycle, indicating right ventricular pressure overload. McConnell’s sign is seen at the top of the right ventricle, with akinesis of the mid-free right ventricular wall and preserved apical contractility. This pattern of regional right ventricular dysfunction is characteristic of acute pulmonary embolism, where the apex appears to bounce like a trampoline while the rest of the right ventricle remains still.
A4CH

A4CH View with Dilated Right Ventricle, Reduced Left Ventricle, and Possible McConnell’s Sign: A4CH view showing a dilated right ventricle and reduced left ventricle. The interventricular septum is flattened, indicating right ventricular pressure overload. A possible McConnell’s sign is visible, with suspected akinesis of the mid-free right ventricular wall and preserved apical contractility, suggesting possible acute pulmonary embolism.